
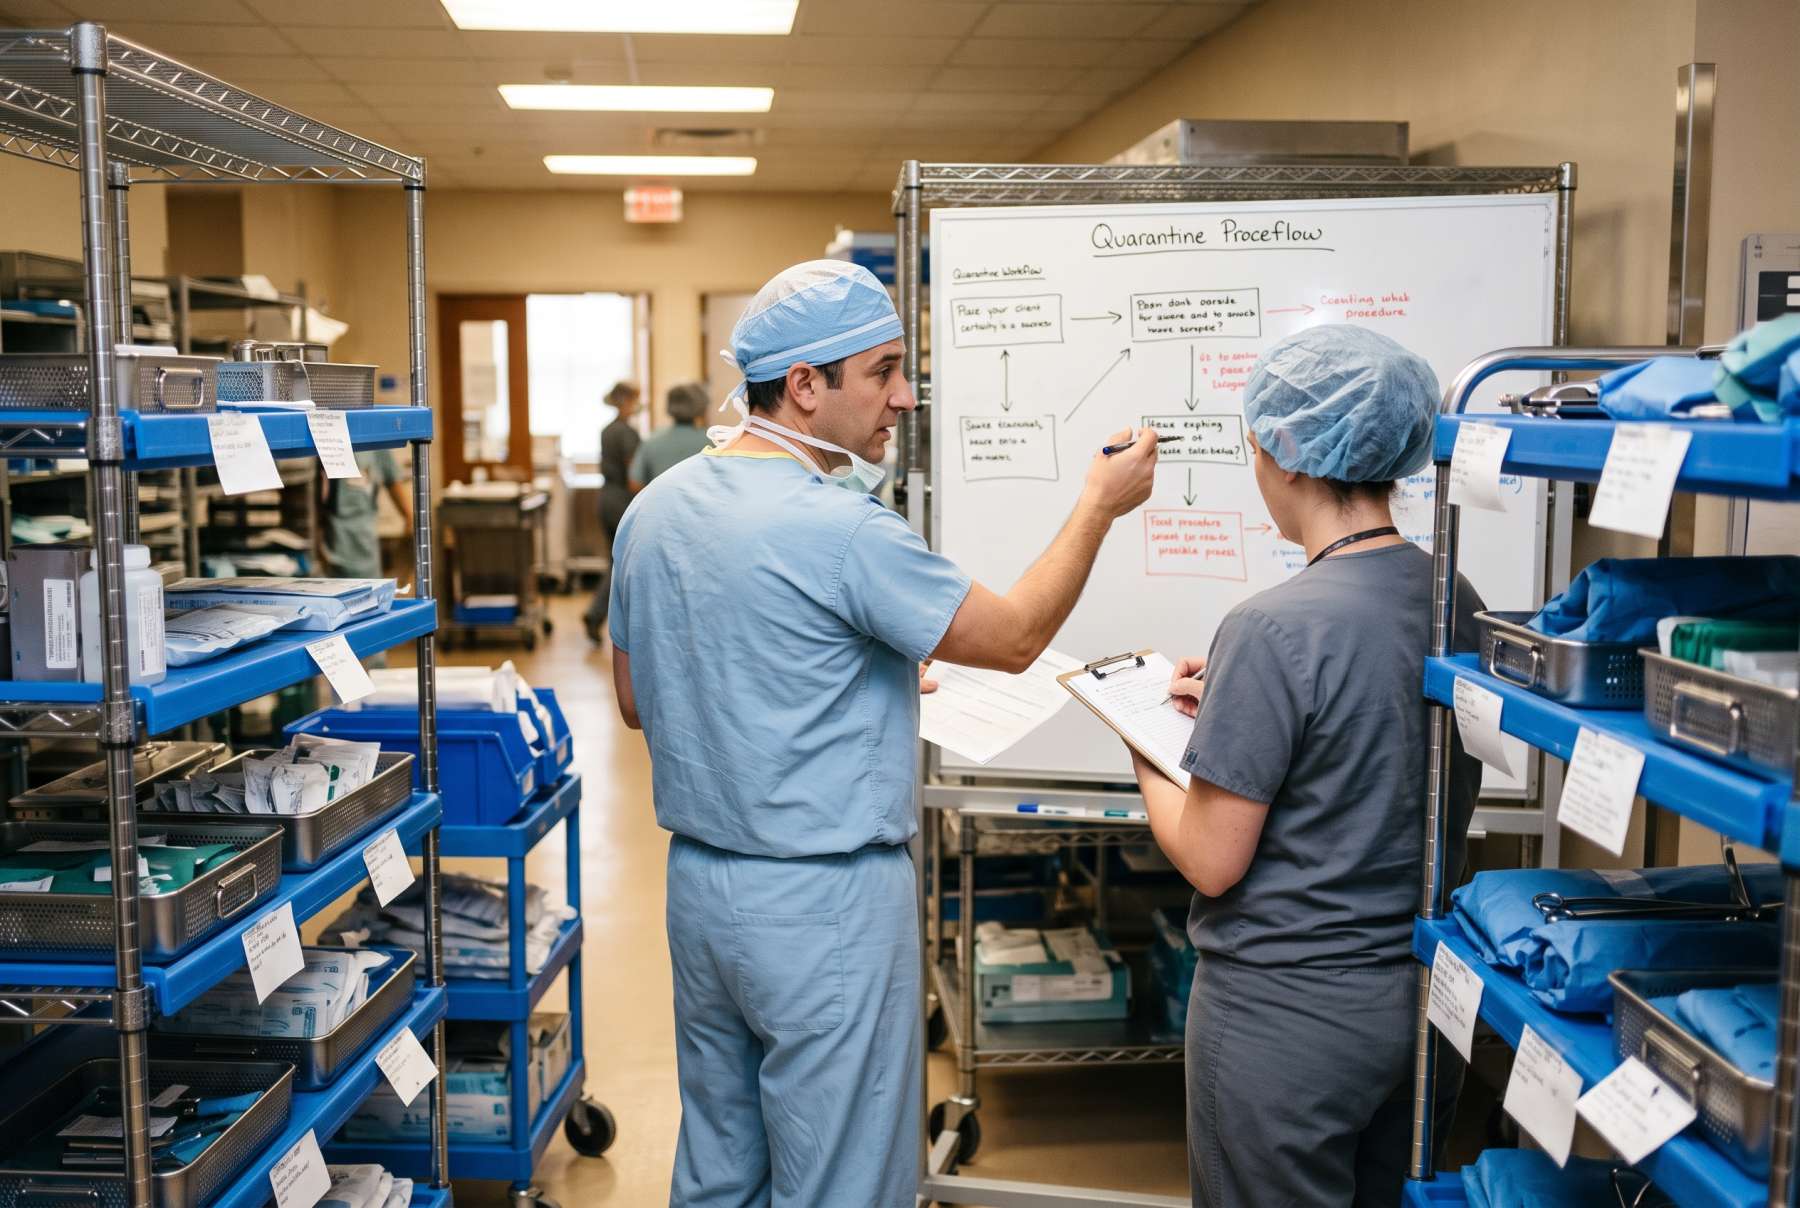
A correction notice can arrive as a letter, an email, a portal update, or a page on a regulator's website. The operational question is less tidy: which physical kits are affected, where are they now, what cases are they assigned to, and who has authority to keep them out of use?
That distinction matters this week. On October 20, 2026, the FDA posted an early alert covering Cardinal Health Presource kits that may contain recalled BD Alaris Pump Infusion Sets. The recommended action is direct: locate and quarantine affected kits, alert clinicians, and label the kit so the affected component is removed before use. If a distributor has further distributed the kits, customers must be notified as well.
On paper, that sounds like an inventory exercise. In practice, it is a status problem. A spreadsheet may tell a team that a kit exists. A shipping record may show that it left the warehouse. A phone call may confirm that a field representative has it. None of those facts, by itself, proves that the kit is quarantined, removed from a case, or cleared for use.
Finding the kit is only the first control
The FDA alert is a useful reminder that a correction is not complete when someone finds the asset. The kit has to move through a chain of decisions.
First, the organization has to identify the affected product. That may mean matching a catalog number, lot, component, kit configuration, or customer distribution record. Then it has to determine the kit's physical location. Is it in a hospital supply room, a 3PL cage, an operating room, a rep's vehicle, a sterile processing holding area, or already in a case cart?
After that comes the part that usually creates the most uncertainty: status. The same kit can be physically present but operationally unavailable. It may be waiting for decontamination, packed for tomorrow's case, in transit to an ASC, or sitting in a warehouse with a quarantine instruction that no one has applied to the record.
Those are not interchangeable conditions. A kit marked as "on hand" can still be restricted. A kit marked as "shipped" can still be inside a hospital. A kit assigned to a case can still be unsuitable for that case. When teams collapse all of those states into a single inventory field, the correction process becomes a series of phone calls and assumptions.
The FDA's companion alert illustrates the same issue from another angle. Some affected Presource kits may require updated use instructions rather than immediate removal of every component. That means the organization needs to know not only where the kit is, but which instruction applies to that specific kit and whether the clinical team has acknowledged the change.
Location, processing status, and case assignment are different facts
Many operations teams already track one of these dimensions. The weakness appears between them.
Location answers, "Where is the asset?" Processing status answers, "What can happen to it next?" Case assignment answers, "Which procedure is depending on it?" Routing priority answers, "What needs attention first?" A correction can change all four without moving the kit an inch.
Consider a loaner tray that is scheduled for a total joint case at an ASC. Before the notice, it may be marked as available and assigned to Thursday's procedure. After the notice, its location is unchanged, but its status should change immediately. The case assignment should be flagged. The routing priority should increase if another tray must be sourced. The field representative, 3PL, hospital supply chain team, and sterile processing department should see the same restriction.
This is where manual systems become fragile. One person updates the warehouse spreadsheet. Another texts the rep. The ASC removes the tray from its preference list. Sterile processing has already received it and is preparing the load. The case coordinator sees only that the tray was delivered. Each person has a partial truth, and the partial truths do not reconcile themselves.
A published policy from AORN's sample loaned instrument workflow shows how many handoffs are involved even without a correction. Loaner items may be checked in, scanned into instrument tracking, matched to a procedure, sterilized under the manufacturer's instructions, scanned to a case cart, verified before the case, decontaminated after use, and scanned out to the vendor. Each handoff creates a chance to attach the correction status to the physical tray.
The operational goal is not to make every team use the same language for its own sake. It is to prevent a restricted asset from looking available simply because its location is known.
The cost of uncertainty shows up before the case
When the status is unclear, teams tend to protect the case by adding time and inventory. A distributor sends a replacement. A 3PL pulls another set. A field representative drives to the hospital to verify what a system should already show. The ASC holds a second kit as a precaution. Sterile processing works around an incomplete handoff.
Those actions may be necessary in an emergency. They are expensive when uncertainty is the default operating model.
The cost is not limited to freight. It includes idle inventory, duplicate preparation, unnecessary sterilization work, staff time spent searching, and the risk that a case team makes a decision using an outdated status. In a device correction, the cost can also include proving what happened afterward. Which kits were located? Which were quarantined? Which had already been used? Which customers were notified? Which assets were cleared, and on what basis?
That last question is often missed. A correction workflow needs a beginning and an end. The beginning is the notice. The end is not simply a completed email campaign. The end is a defensible asset record showing the affected item, its location, its restriction, its case impact, its corrective action, and its release or removal.
For distributors and 3PLs, this is especially important because the physical asset may cross several organizations without changing ownership. The FDA's October alert specifically notes that distributors must notify customers if affected kits were further distributed. A shipment history can identify the customer, but it may not reveal whether the kit is still in that customer's warehouse, has moved to an ASC, or has been opened for a scheduled procedure.
For hospitals and ASCs, the problem runs in the other direction. The organization may know the kit is in the building, but not whether the supplier's restriction has been applied to the case cart, the sterile processing queue, or the local inventory record.
A better measure is time from notice to controlled status
Most teams can report that a correction was received. Fewer can answer how long it took to place every affected asset into a controlled status.
That is the metric worth adding. Measure the time from the correction notice to the point at which each affected asset is located, restricted, linked to any impacted case, and assigned an owner for the next action. Do not treat a mass email as completion. Do not treat a warehouse count as quarantine. Do not treat a phone confirmation as proof that the status followed the tray.
The system does not need to replace clinical judgment or the manufacturer's instructions. It needs to make the operational facts visible. A tray or loan set should carry its identity through warehouse, hospital, ASC, sterile processing, and the field. Its location should update without relying on a manual hunt. Its case assignment should be visible to the people protecting the schedule. Its status should remain distinct from its location.
That is also why a tag that stays with the asset through sterilization matters. If visibility disappears at decontamination, the correction record can lose contact with the physical tray at the exact point when processing status becomes important. The same principle applies to loaner kits, implant totes, and other assets that move between organizations under time pressure.
The sharper way to view a correction is not as a document problem. It is a controlled movement problem. The question is not only whether the organization received the notice. It is whether the right physical asset became unavailable to the wrong case, whether everyone involved could see that change, and whether the organization can prove what happened next.
A correction notice starts the clock. Visibility is what stops the uncertainty.


